Acute fissure
A newly developed tear, often after a hard stool, with sharp pain or fresh bleeding.
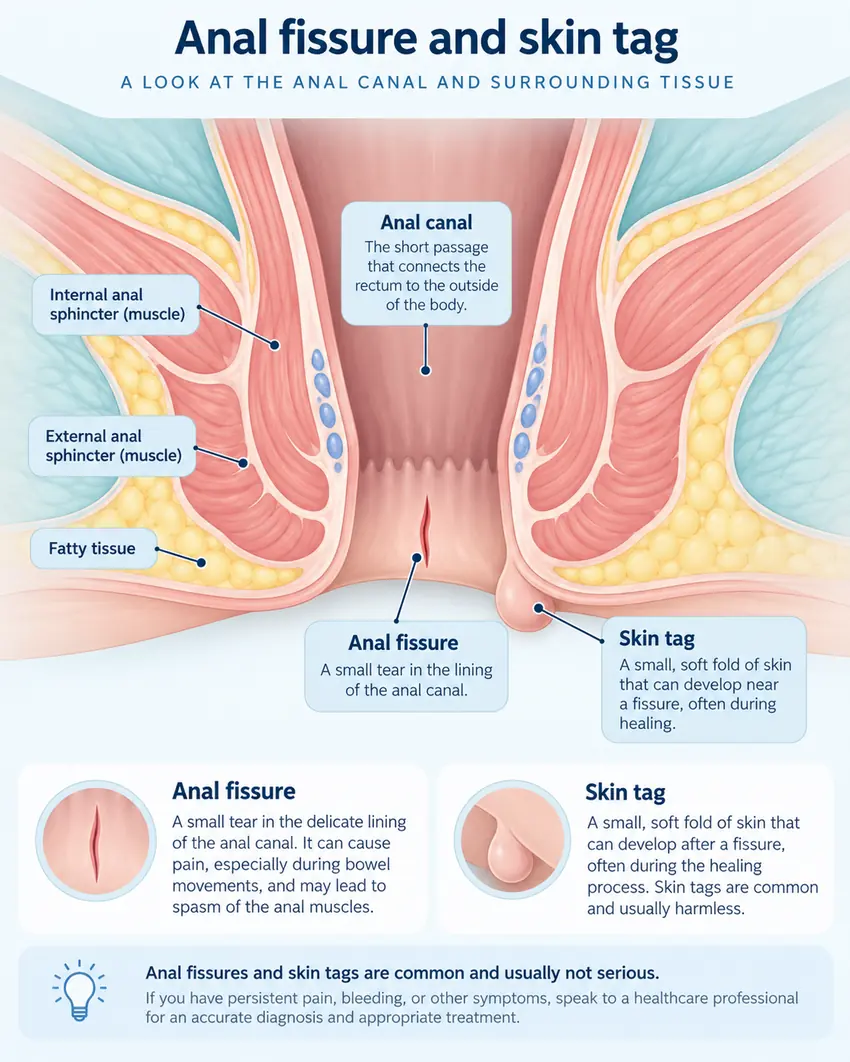
An anal fissure is a small tear in the lining of the anal canal. It can cause sharp pain during bowel movements, burning afterwards, and a little bright-red bleeding. Many fissures heal with stool regulation and medicines—surgery is not always needed.

Seek urgent care for heavy or persistent bleeding, fainting, black stools, severe swelling with fever or pus, or severe worsening pain. New or recurring bleeding, anaemia, unexpected weight loss or changes in bowel habits require proper evaluation.
Symptoms often follow a distinct pattern but still need confirmation by examination.
A cutting, tearing or stinging sensation while passing a bowel movement.
Common symptomDiscomfort or spasm may continue for minutes or even hours after passing stools.
Typical patternSmall amounts may be seen on toilet paper or on the stool surface. Other causes must be excluded.
Needs evaluationHard stools can worsen a tear; avoiding bowel movements can perpetuate the cycle.
Often contributesIllustrations are simplified for public education; appearances can vary.
An anal fissure is a small tear or ulcer in the lining near the opening of the anal canal. A hard stool or repeated bowel irritation can trigger it.
A tear develops
Hard stools, straining or frequent loose stools can injure the sensitive lining.
The muscle tightens
Pain may trigger internal anal sphincter spasm, which can reduce local blood supply.
Healing can be delayed
Persistent spasm and repeated trauma can lead to a chronic fissure.
How long the fissure has been present and how it looks on examination influence the treatment plan.
A newly developed tear, often after a hard stool, with sharp pain or fresh bleeding.
A persistent or recurrent tear, sometimes with a sentinel skin tag, local scarring or significant sphincter spasm.
Regular, soft bowel movements are central to healing and to reducing recurrence.

Yes—many acute fissures improve with conservative measures. The first aim is to keep stools soft and reduce painful spasm without further injury.
Seek medical assessment if pain or bleeding is worsening, persists, or repeatedly returns. Self-care does not replace evaluation of unexplained bleeding.
Not all patients need a procedure. The best option depends on chronicity, symptoms, sphincter function and previous treatment.
| Approach | When considered | What it aims to do | Important consideration |
|---|---|---|---|
| Diet, fibre & stool regulation | Most acute fissures; ongoing care for chronic fissures | Keep stools soft and prevent repeated trauma | May take consistent daily habits |
| Prescription topical medication | Persistent symptoms or chronic fissure | Diltiazem or nifedipine preparations, or glyceryl trinitrate, may help relax the internal sphincter | Medicines need clinician guidance; nitrates may cause headache |
| Botulinum toxin | Selected chronic fissures, often after inadequate response to medicines | Temporarily reduce sphincter spasm | Results vary; temporary changes in continence can occur |
| Lateral internal sphincterotomy | Selected persistent chronic fissures | Reduce sphincter pressure to allow healing | Potential continence-related risks need careful assessment |
| Other / laser-assisted procedures | Selected circumstances after discussion | Treat specific tissue when appropriate | Laser is not a routine first-line requirement or proven replacement for established therapies |
Before surgery, discuss prior childbirth-related injury, previous anorectal surgery, existing continence problems and other relevant conditions with your surgeon.
The examination is guided by your symptoms and comfort. A painful internal examination is not always necessary at the initial visit.
Duration of pain, bleeding, bowel habits, childbirth, previous treatments and relevant medicines.
A fissure and a sentinel skin tag may be visible without an uncomfortable examination.
Digital rectal examination or proctoscopy may be deferred when very painful, or considered later if appropriate.
Multiple or unusual fissures, fever, discharge, persistent bleeding or bowel changes may require further tests, including colonoscopy in selected patients.

Whether treated medically or surgically, avoiding hard stools and straining remains important.
Vegetables, fruit, pulses and whole grains can support soft, regular stools.
Hydrate appropriately for your health needs, particularly when increasing fibre.
Go when you feel the urge; avoid excessive straining or long toilet sessions.
Persistent, recurring or atypical symptoms deserve clinical review rather than repeated self-treatment.

Consultant Surgeon · Laparoscopic & Bariatric Surgery
MBBS · MS (General Surgery) · FMAS · DMAS · SAGES (USA) · WALS (UK)
Patients with anal pain need a precise diagnosis—not an automatic recommendation for laser treatment or surgery. Management is selected to relieve symptoms, encourage healing and protect sphincter function wherever possible.
Simple answers before your consultation.
It is a small tear in the lining of the anal canal. It can cause sharp pain with bowel movements, burning afterwards and sometimes a little bright-red blood.
No. Piles are enlarged haemorrhoidal cushions, while a fissure is a tear in the lining. Symptoms can overlap, so the cause should be examined.
Yes. Many new or acute fissures heal with soft stools, fibre, adequate fluids, warm baths and appropriate medical treatment.
A fissure can trigger spasm of the internal anal sphincter, so pain may continue after the bowel movement.
An acute fissure is recent, typically less than six weeks. Chronic fissures persist longer or show established changes such as a sentinel skin tag or scarring.
It is a small skin fold that can appear at the outer end of a long-standing fissure. It does not necessarily require removal.
Prescription topical preparations may help selected chronic fissures heal by reducing sphincter pressure. Your clinician will choose the medicine and discuss possible side effects.
Botulinum toxin may be an option for selected chronic fissures, often when topical treatment has not been sufficient. Healing and side effects vary.
No. Many people first try medical treatment. Persistent fissures may be assessed for injection or surgery depending on the findings and personal risk factors.
No. Laser is not routinely necessary for fissures. Established options include stool regulation, topical medicines, Botox and selected sphincter surgery; a laser-based technique may be discussed only where appropriate.
Yes. Recurrent constipation, hard stools, diarrhoea or repeated trauma can cause symptoms to return.
Bleeding that is heavy, persistent, recurrent or associated with changes in bowel habits, anaemia, black stools or unexpected weight loss needs medical assessment rather than assuming it is a fissure.
Request a consultation for anal pain, burning or rectal bleeding. You do not need to send sensitive symptoms via WhatsApp to arrange an appointment.
Shri Ramdev Healthcare Center · Shop No. 1, Golders Green Building No. 1, Holy Cross Road, IC Colony, Borivali West, Mumbai – 400103.
ASCRS patient guidance · ASCRS Anal Fissure Guidelines (2023) · NHS Anal Fissure